Shedding, shock loss and the three-month low point are all expected — here is the sequence and when you can judge the result
The single most useful thing to know before a hair transplant is that the transplanted hairs fall out, and that this is normal. Patients who are not told this in advance spend the third month convinced the operation has failed. The timeline below is the sequence most surgical teams describe, and it is worth reading before you book rather than after.
The first two weeks
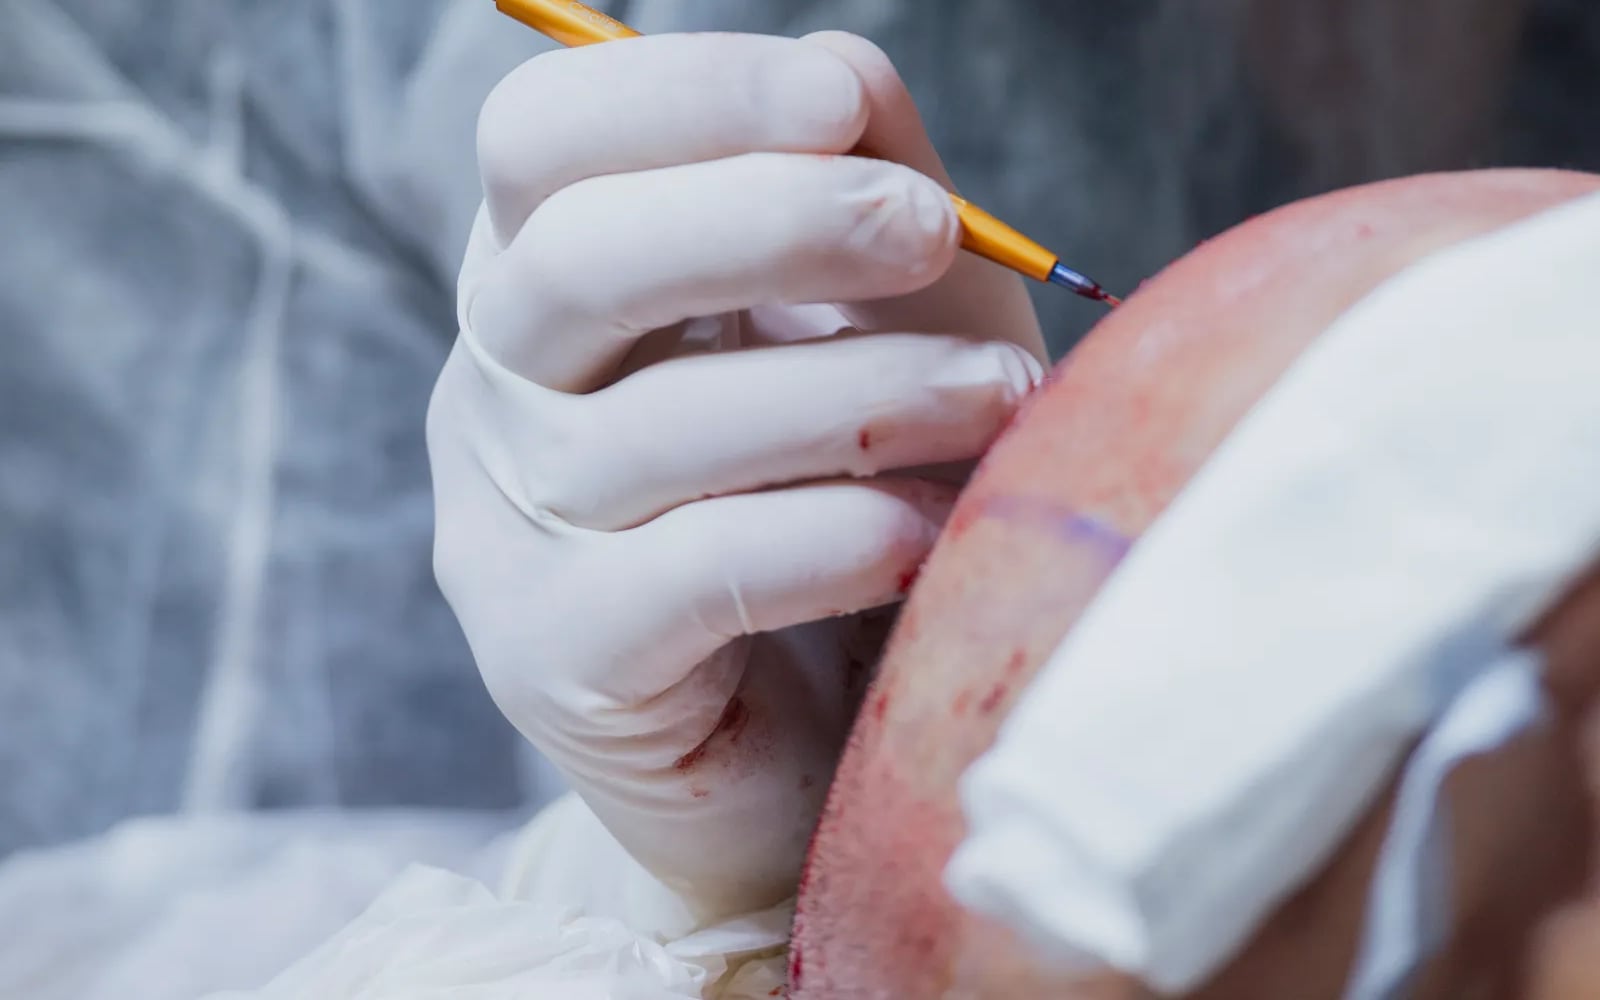
Crusts form over the recipient sites within about 24 hours. Swelling of the forehead typically peaks around day three and settles over the following three to four days; ice is applied to the forehead, never to the grafted area. Crusts shed somewhere between day four and day 14. If you had a strip procedure, sutures come out at 10 to 14 days.
Most people take one to two weeks away from work, mainly because of the visible crusting and redness rather than because of pain or restriction. Washing begins after 24 hours, without rubbing. Full immersion — baths, pools, the sea — is generally avoided for two to four weeks. Sleeping with the head elevated 15 to 30 degrees is usual in the first week, heavy lifting is avoided for the same period, brushing resumes after about a week, and haircuts and dye are usually deferred for a month. Direct sun is avoided for around a month.
These protocols are expert consensus rather than trial-derived, so they legitimately vary between surgeons. If your team's instructions differ from something you read online, follow your team's.
Weeks two to eight: the shedding phase
Between roughly two and eight weeks, the transplanted hairs shed. The follicle stays; the hair shaft it was carrying does not. This is the expected behaviour of a transplanted follicle entering a resting phase, not a sign of graft loss.
Separately, some of the native hair surrounding the grafts may also shed — shock loss — beginning anywhere from two to six weeks. This is where the published numbers become unreliable. Reported incidence spans from 0.10 per cent to "most patients" depending entirely on how each study defined it, so no defensible figure exists. What can be said honestly is that it is common, usually mild, temporary, and generally resolves over three to six months. Be sceptical of any clinic quoting you a precise shock-loss rate.
Months three to six: the low point, then the turn
Dormancy typically ends around 10 to 14 weeks, and new growth begins at three to four months. Before that, at around three months, the treated area may genuinely look thinner than it did before surgery — the transplanted hairs have gone and the native hairs affected by shock loss have not yet returned. This is the expected shape of the curve, and it is the point at which patients most often lose their nerve.
New hairs emerge fine and often lighter in colour, then thicken over subsequent cycles. Growth is not uniform across the scalp; patchiness at four or five months is not a meaningful signal.
Months six to eighteen: the result
Most patients see their result between six and nine months. The final result — full thickness, settled texture, the last of the density — is generally placed at 10 to 18 months. That is also the window in which any second session would be discussed, if one is planned.
Second sessions are common enough to plan for. In the profession's own global census, the mean was 2,176 grafts for a first procedure and 1,641 for a subsequent one, with a mean of 1.4 procedures overall; 68.2 per cent of surgeons reported one procedure on average. Among patients with advanced loss, 62 per cent wanted a second session, and 9 per cent reported some loss of density by 24 months.
What runs alongside the timeline
Medical therapy is usually part of the plan rather than an alternative to it. Minoxidil is typically stopped a week before surgery and restarted, at 5 per cent twice daily, around five to seven days afterwards. Finasteride at 1 mg per day is continued indefinitely, with side effects put under 2 per cent in ISHRS material. Both stop working when you stop taking them — that is the point people most often miss. Consensus is that surgery should generally follow at least 12 months of medical therapy without improvement.
Smoking is the one preparation item with a hard finding attached: in a single-centre series of 2,896 patients, the only cases of recipient-area necrosis occurred in smokers. Stopping three to six weeks before surgery is the usual advice. Alcohol is avoided for three days beforehand and anti-inflammatory painkillers for seven.
Reading your own progress honestly
Take a photograph in the same light, at the same angle, once a month. Month-to-month change is small enough that memory is a poor instrument, and the comparison you will want at month eight is with month four, not with a vague recollection of how things looked.
The hair transplant page sets out how follow-up is structured, and the practical side of the trip — how long you stay, what the first wash involves — is covered under hair transplant in Turkey and in packages and prices.
Your own timeline will depend on your donor area, the extent of the area treated, your age and whether you are on medical therapy, so treat the months above as a shape rather than a schedule. Send photographs of your hairline, crown and donor area through our contact page and we will assess your case individually, at no cost, and tell you plainly what a realistic result looks like in your situation.