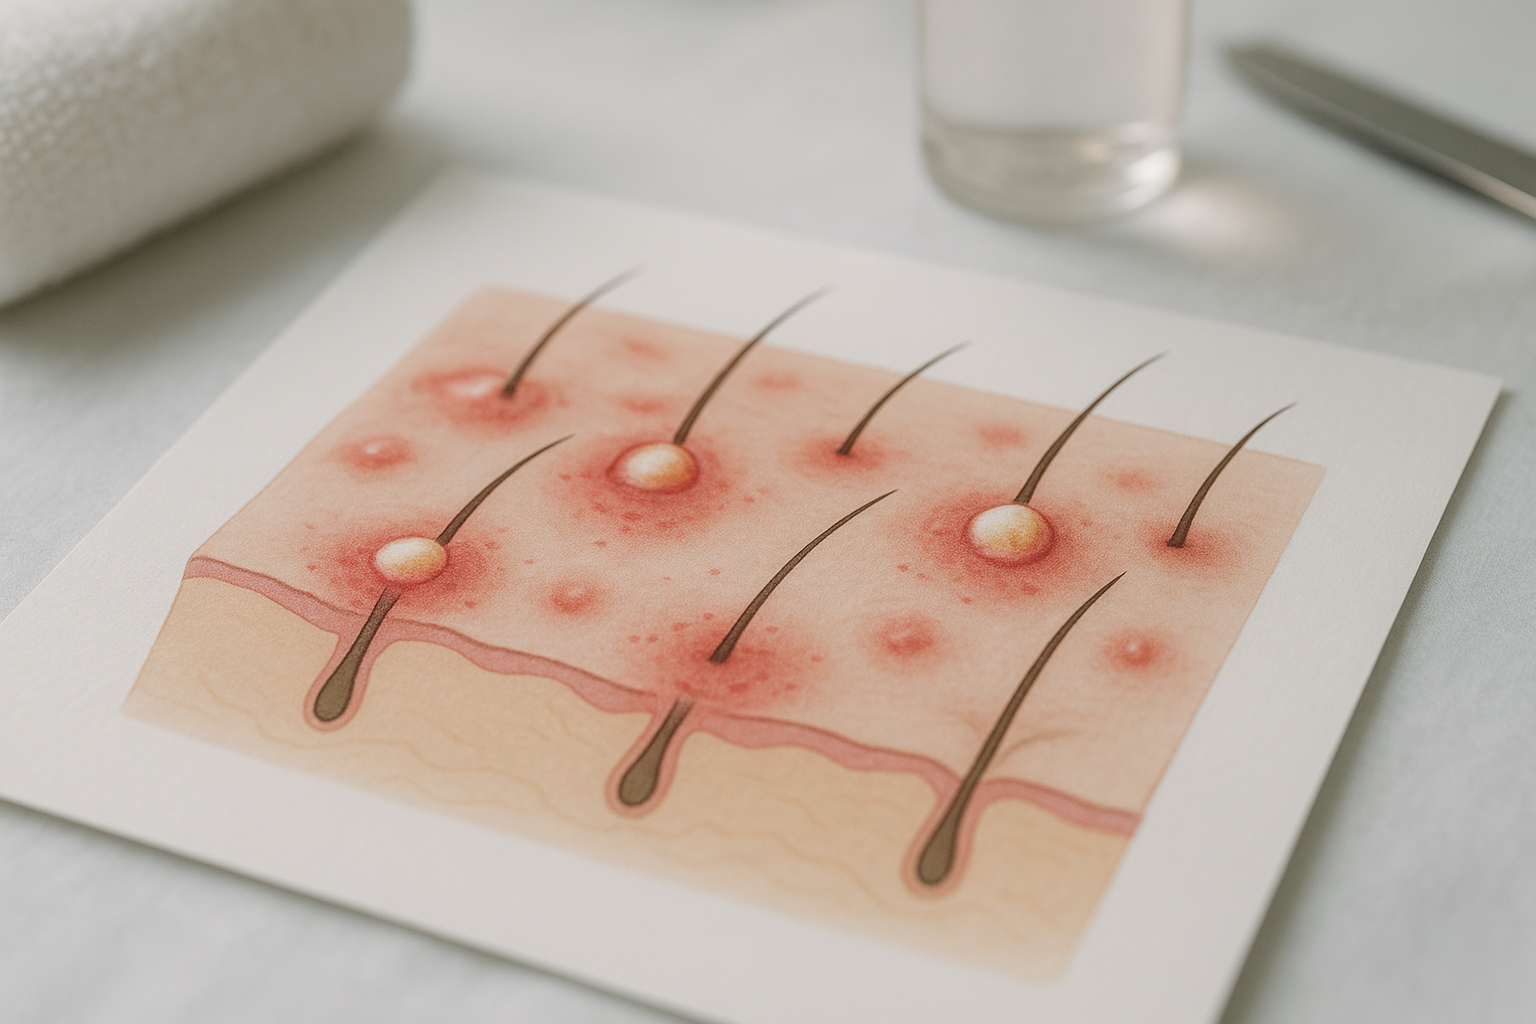
Some vitamin and mineral deficiencies—especially iron, D, B12, and zinc—can contribute to hair shedding, but the true cause must be confirmed by a doctor before trying supplements.
Several vitamin and mineral deficiencies—especially iron, vitamin D, B12, and zinc—can contribute to hair loss, but only after a medical diagnosis can the underlying cause be confirmed.
How Nutrients and Deficiency Affect Hair Follicles
Vitamins and minerals essential for hair growth
Hair follicle cells divide rapidly and need a consistent supply of nutrients. Important vitamins and minerals for normal hair growth include iron, vitamin D, vitamin B12, biotin, zinc, copper, niacin (vitamin B3), folate, and essential fatty acids. Each serves a specific role: iron helps transport oxygen to follicles; vitamin D influences follicle cycling and immune function; B12 and folate are needed for cell division; biotin supports keratin production; zinc and copper are involved in enzymatic processes and protein structure; niacin aids blood flow; and fatty acids maintain the scalp barrier. Even mild deficiencies can disrupt this balance. If you are interested in how different hair restoration techniques work alongside nutritional support, you can learn more about the Percutaneous Sapphire technique or the DHI method.
How deficiencies disrupt the hair growth cycle
The hair growth cycle includes three phases: anagen (growth), lasting 2–6 years; catagen (transition), about 2–3 weeks; and telogen (resting and shedding), which lasts 2–4 months. When certain nutrients are lacking, more follicles may shift prematurely from anagen to telogen—this is called telogen effluvium and usually leads to diffuse shedding weeks or months after the trigger.
For instance, lower iron or vitamin D may increase hair fall, while not enough zinc or biotin can weaken hair shafts. Excesses, such as too much vitamin A or selenium, can also lead to shedding; both deficiency and oversupply have risks. To understand why these factors can be especially important for women, see hair loss in women and how the approach differs. Balanced nutrition—neither too little nor too much of any nutrient—matters for scalp and hair health.
Specific Deficiencies Linked to Hair Shedding
Iron, vitamin D, and B12: prevalence and impact
Iron deficiency is frequently linked with hair loss, especially in premenopausal women. Iron is needed for hemoglobin, which delivers oxygen to hair follicles. Ferritin, the storage form of iron, is often measured; values below 30 ng/mL may be considered low in cases of hair shedding, though specific laboratory standards vary. Vitamin D, produced in the skin through sunlight and obtained from diet, plays a role in follicle cycling. Low vitamin D is common in areas with less sunlight, and levels under 20 ng/mL are typically seen as insufficient. Vitamin B12 deficiency is more often found in vegetarians, vegans, and older people; symptoms can include hair changes and neurological signs, with levels below 200 pg/mL often considered low.
Other nutrients: biotin, zinc, copper, niacin, and more
Biotin deficiency is rare but possible in people with genetic predispositions or those taking certain long-term antibiotics. It may cause thinning hair, brittle nails, and sometimes skin rashes. Zinc is essential for protein synthesis; levels below 70 mcg/dL could be associated with more shedding, particularly in those who avoid animal products. Copper is necessary for keratin fiber cross-linking and may be low in some with absorption problems. Niacin deficiency (pellagra) is uncommon but leads to skin and hair changes. Essential fatty acids and folate (with red cell folate levels under 140 ng/mL considered low) also help support hair health. For women experiencing ongoing shedding despite correcting diet, discussing hair transplant options for women with a clinician may be appropriate as part of a broader management plan.
| Nutrient | Typical Blood Test | Common Sources | Hair Loss Pattern | Who Is Most at Risk |
|---|---|---|---|---|
| Iron | Ferritin, hemoglobin | Red meat, lentils, spinach | Diffuse shedding | Women of reproductive age |
| Vitamin D | 25(OH)D | Sunlight, oily fish, eggs | Diffuse thinning | Limited sun exposure, older adults |
| Vitamin B12 | Serum B12 | Meat, dairy, fortified foods | Diffuse loss, brittle hair | Vegetarians, elderly |
| Zinc | Serum zinc | Meat, shellfish, seeds | Diffuse, brittle strands | Malabsorption, restrictive diets |
| Biotin | Serum biotin (rarely tested) | Eggs, nuts, whole grains | Patchy or brittle loss (rare) | Genetic enzyme deficiency |
When to Suspect Deficiency-Related Hair Loss
Distinguishing signs and patterns
Diffuse thinning across the scalp, rather than receding at the hairline or crown, is more typical when hair loss is linked to vitamin deficiency. You may notice increased daily shedding—sometimes more than 100 hairs, especially during washing or brushing. Other clues can include chronic fatigue, nails that are brittle or ridged, and pale skin, all of which may point to a deficiency affecting more than just hair.
Deficiency-related hair loss rarely causes visible scalp inflammation or scarring, unlike some other forms. Hair may become softer, more fragile, or break more easily, but the scalp usually appears normal. Both men and women can develop this diffuse loss, and regrowing hair may look finer or grow more slowly for a period. To see outcomes in different types of hair loss, review examples of real patient results from various causes.
Risk factors and who is more likely affected
Some people are more likely to experience deficiency-related hair loss. Adults on restrictive diets—such as vegan, vegetarian, or very low-calorie regimens—may lack key micronutrients like iron, B12, or zinc. Medical conditions that reduce nutrient absorption, including celiac disease, inflammatory bowel disease, or history of bariatric surgery, also increase risk. Rapid weight loss, due to dieting or illness, can trigger telogen effluvium, leading to increased shedding.
Women with heavy menstrual periods or those who are pregnant may develop iron deficiency, which can cause more hair to shed. Chronic illnesses, untreated thyroid problems, or long-term digestive disorders may also lower vitamin and mineral reserves. Recognizing these risk factors can help you and your clinician decide when to look beyond age or genetics as a cause of hair loss.
Diagnosis: Why Testing Is Essential Before Supplements
Medical evaluation and lab tests
Unexplained hair loss warrants a thorough medical evaluation. Physicians typically start with a detailed history, asking about recent illnesses, diet, medications, menstrual or pregnancy status, and rapid changes in weight. The physical exam focuses on the scalp's hair distribution and checks nails and skin for broader deficiency signs like pallor or brittleness.
Lab tests can identify deficiencies contributing to hair loss. Common tests include serum ferritin (for iron stores), vitamin D, B12, zinc, and a complete blood count (CBC) to check for anemia or infection. Thyroid stimulating hormone (TSH) is also measured, since thyroid problems can mimic or add to hair shedding. These findings help guide safe management. If you are interested in how hair typically regrows after causes are addressed, see the month-by-month hair transplant recovery timeline, though regrowth rates differ when the cause is nutritional.
Risks of self-treating with supplements
Starting vitamin or mineral supplements without lab confirmation can sometimes cause harm. High doses of iron, vitamin A, or zinc may result in toxicity, with symptoms from digestive upset to more severe health effects. Self-medicating might also hide underlying medical conditions, delaying an accurate diagnosis.
Certain supplements, such as biotin, can interfere with blood test results—especially thyroid and heart markers—giving misleading information. Only a physician can interpret your symptoms, bloodwork, and health history in context to determine if supplementation is needed or if another cause should be investigated first.
Treatment, Diet, and Potential for Hair Regrowth
Correcting deficiencies through food and supplements
Restoring nutrient balance typically begins with dietary changes, focusing on nutrients like iron, vitamin D, biotin, and zinc. For iron deficiency, including lean red meat, lentils, and spinach in your meals helps, especially when combined with vitamin C sources such as bell peppers or oranges to enhance absorption. Keep in mind that calcium can compete with iron for absorption, so taking them at different times may be beneficial if both are needed. With other micronutrients, such as zinc and copper, high doses of one can interfere with the other’s absorption. Supplementation is sometimes necessary, but the type and dose should always be personalised and supervised by a physician. Over-the-counter multivitamins may not address your specific deficiency and are not always indicated. In some cases, injectable forms like vitamin B12 are needed if gastrointestinal absorption is impaired. Blood levels are usually checked by your doctor both before and after starting supplements to monitor your progress. If you wish to see examples of outcomes after different treatments, you can review results from previous patients on our website.
What to expect after repletion: timelines and limits
After correcting a nutritional deficiency, hair shedding generally improves within 2 to 6 months, reflecting the time needed for hair follicles to transition from the resting (telogen) to the growing (anagen) phase. Some regrowth may appear in a few months, but how much returns depends on the duration and severity of the deficiency, and whether follicles have been permanently affected. Early treatment tends to offer a higher chance for visible improvement. If hair loss has lasted more than a year or if scarring is present, full regrowth is less likely. Not all hair will necessarily return, especially if other factors are involved. If recovery is incomplete, non-nutritional options such as surgical treatments may be discussed. You can read about how the number of grafts needed is estimated in our detailed explanation of graft calculation and donor limits. The final decision about any treatment is made by your examining physician after a thorough evaluation.
Who Should Not Rely Solely on Vitamin Treatment
Situations where deficiency is unlikely
Many forms of hair loss are not caused by vitamin or nutrient deficiencies. Hereditary conditions such as male and female pattern baldness (androgenetic alopecia) usually do not respond to vitamin supplementation. Scarring alopecias, including lichen planopilaris, cause permanent follicle loss that cannot be reversed by correcting micronutrient levels. Additionally, chronic medical issues—such as well-controlled thyroid disease or longstanding scalp infections—often require targeted medical or dermatological therapies. Relying on vitamins alone in these cases may delay more effective treatment and allow the underlying cause to progress.
When to seek specialist advice
If you notice rapid hair loss, patchy or uneven thinning, visible scarring or scaling on the scalp, or symptoms like fever, joint pain, or unexplained weight changes, consult a dermatologist or specialist. Persistent shedding that continues beyond six months, unexplained thinning, or any hair loss causing discomfort also should be evaluated by an expert. The examining physician will review your medical history, conduct a scalp assessment, and may order laboratory tests to clarify the diagnosis. In cases where follicles are no longer viable and advanced procedures are considered, you can discuss options such as the Percutaneous Sapphire hair transplant technique with your doctor. Surgical interventions are only offered after all other causes have been ruled out and a realistic plan has been established for your particular situation.
Frequently asked questions
-
Iron, vitamin D, and vitamin B12 deficiencies are the most frequently associated with hair shedding. Zinc and, far less commonly, biotin or copper deficiencies may also contribute. The likelihood and severity depend on your medical and dietary background.
-
Yes, excessive intake of certain vitamins and minerals—especially vitamin A and selenium—can trigger hair shedding. For this reason, supplements should only be started after blood tests confirm a deficiency.
-
Deficiency-related hair loss usually causes diffuse thinning and increased daily shedding, rather than the patterned thinning seen in genetic hair loss. Only a healthcare professional can distinguish the causes for sure, often using blood tests and a clinical exam.
-
Biotin deficiency is rare in adults who eat a varied diet. Most people with hair loss do not have a biotin deficiency, so routine supplementation is rarely needed unless a specific medical reason is found.
Sources
- British Association of Dermatologists
- American Academy of Dermatology
- Journal of the American Medical Association (JAMA) Dermatology