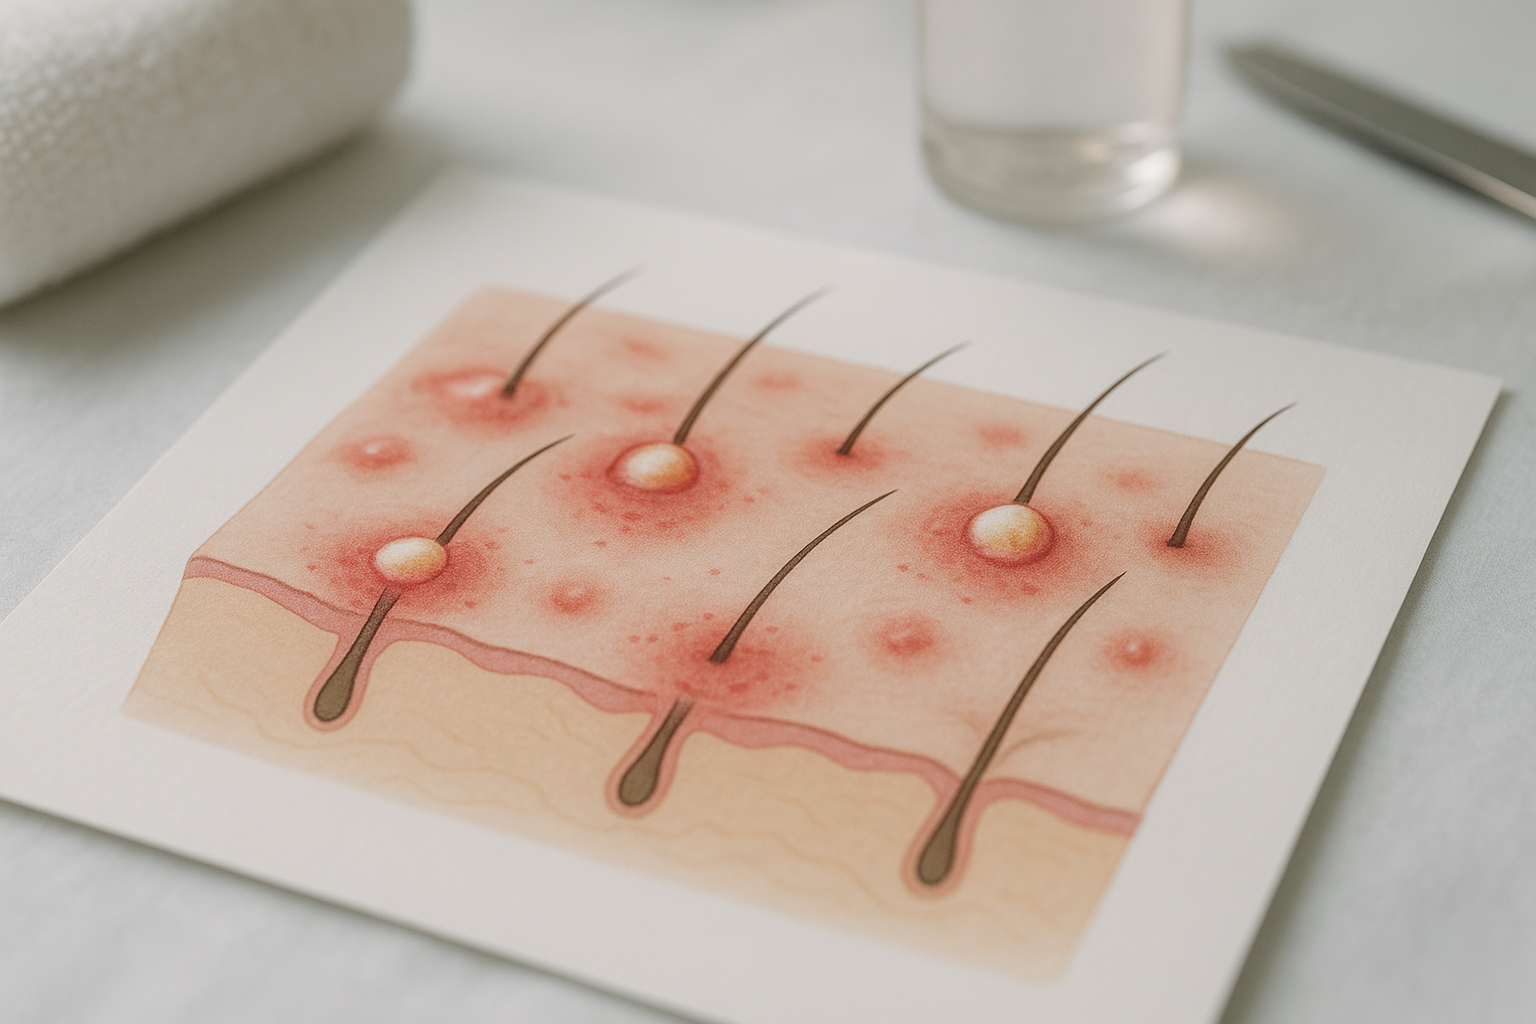
Understand the difference between shedding, thinning and breakage before considering treatment or travelling to Türkiye.
Female hair loss can arise from inherited thinning, hormonal changes, illness, nutritional deficiencies, immune conditions or hair damage, and an examination helps distinguish these causes.
A widening part and bare patches suggest different causes
Inherited thinning, age and hormonal changes
You may notice more scalp along your part while the frontal hairline remains largely unchanged. This gradual thinning across the part and crown differs from separate bare patches or a frontal edge that moves backwards. These patterns offer clues, but appearance alone cannot establish the cause.
The American Academy of Dermatology describes a widening part or reduced fullness as common ways female pattern hair loss becomes noticeable. It can begin in the twenties or thirties and becomes more common with age. Inherited sensitivity within the follicles gradually shortens hair growth and produces progressively finer hairs. This does not mean every affected woman has raised androgen levels; thinning can develop despite hormone measurements being within their usual ranges.
Around menopause, hormonal changes can accompany reduced hair fullness, alongside age-related changes. If thinning occurs with irregular periods or increased facial hair, polycystic ovary syndrome, or PCOS, is one possible contributor for a clinician to investigate. Neither thinning nor these accompanying features establish that diagnosis on their own.
Immune conditions and inflammation of the scalp
Round or oval bare patches can occur with alopecia areata, in which the immune system targets hair follicles without usually destroying them. Frontal fibrosing alopecia follows a different pattern: it can move the frontal hairline backwards and affect the eyebrows. It involves scarring, which can permanently damage follicles. A receding edge therefore deserves medical assessment rather than being assumed to reflect inherited thinning.
Itching, redness and scale suggest another set of possibilities. Eczema and psoriasis can inflame the scalp, encourage scratching and contribute to shedding or breakage. They are not interchangeable with female pattern hair loss, although scalp inflammation and inherited thinning can occur together.
Small spots centred on individual hairs differ from broader areas of flaky skin. Folliculitis may produce tender or pus-filled bumps around follicles; how folliculitis develops and what may ease symptoms explains this distinction. Because bumps, scale and hair loss can overlap, an examining clinician needs to assess the scalp before deciding what they represent.
Shedding can follow events you have already recovered from
Stress, illness, childbirth and surgery
By the time extra hair appears in your shower or brush, the event that triggered it may already feel distant. Increased shedding often begins around 2–3 months after a trigger, although this timing is a clinical clue rather than a diagnostic rule. In telogen effluvium, a physical or psychological stressor shifts more follicles into their resting phase; those hairs are then shed later.
The British Association of Dermatologists identifies illness, major stress, childbirth and marked weight loss as possible triggers for telogen effluvium. After childbirth, changes in the hair-growth cycle can lead to noticeable shedding even without another illness. Following surgery, the physical stress of the operation, blood loss and reduced food intake during recovery may all contribute. Anaesthesia alone should not be assumed to explain the change.
There is no single postoperative remedy that addresses every cause. The useful next step is to identify ongoing contributors, support recovery and have persistent shedding assessed. The course differs depending on whether the trigger has resolved, nutritional gaps remain or inherited thinning is also present.
Thyroid problems, nutritional gaps and treatment effects
An underactive or overactive thyroid can disturb the hair-growth cycle. Iron deficiency may contribute with or without anaemia, while restrictive diets and inadequate protein intake can leave too little nutritional support for growth. Low vitamin D may warrant assessment in context, but a low result alone does not establish why your hair is falling out.
Some medicines cause delayed shedding through changes in the resting cycle. Certain cancer treatments can instead interrupt actively growing hairs, producing more rapid and sometimes extensive loss. The treatment involved and the timing of the change help your clinician distinguish these mechanisms.
Visible shedding can affect confidence, social life and how comfortable you feel styling your hair. That distress is real, but it does not mean emotional stress explains every case. You can discuss both the shedding and its impact with your usual clinician. Counselling or peer support are optional sources of help alongside, rather than substitutes for, assessment of the physical causes.
Colouring and tight hairstyles affect hair in different ways
What dye changes, and what a reaction can do
Yes, dye can damage the hair shaft and contribute to breakage. An irritant or allergic scalp reaction may also contribute to shedding. Ordinary colouring, however, is not an established cause of inherited follicle miniaturisation—the gradual production of finer hairs.
In permanent colouring, alkaline ingredients help open the hair’s outer layer, while peroxide supports colour development or lightening. Repeated processing can leave lengths fragile, particularly where lightener overlaps previously treated hair.
The NHS states that para-phenylenediamine, or PPD, in some hair dyes can cause allergic reactions. Allergy involves an immune response; irritation from ingredients such as peroxide or ammonia can cause burning or soreness without an allergy. Symptoms may overlap, so appearance alone cannot reliably distinguish them.
A “natural” label does not rule out a reaction, and black henna products may contain PPD. There is no universal colouring interval: follow product instructions and consider your scalp condition, previous reactions and existing breakage. Follow the manufacturer’s allergy-testing instructions, but do not treat a negative check as certainty. Avoid dye on an inflamed scalp; after a previous reaction, seek medical advice before using it again.
Traction, breakage and environmental exposures
Tight braids, extensions and tightly secured styles repeatedly pull on follicles. They may also snap shafts. Early traction-related loss may improve after tension stops, whereas longstanding pulling can scar follicles and leave lasting loss. Tenderness or bumps around a tight style are reasons to loosen it rather than tolerate the pulling.
Once damaged, a shaft cannot biologically repair itself. Conditioners may improve its surface feel, but visible improvement depends on reducing further damage and growing out or trimming affected lengths. Looking at hair restoration photographs cannot tell you whether your own shorter hairs reflect breakage or regrowth, or predict your response.
Hard-water mineral deposits may affect how hair feels and how easily it can be managed. Evidence does not establish hard water as a cause of female pattern hair loss. Dryness, tangling and follicle changes therefore need separate consideration rather than being attributed to the same exposure.
An examination should come before a treatment shortlist
What the physician looks for
During your visit, the physician inspects the scalp directly and may use a dermatoscope, a magnifying instrument, to examine follicle openings and surrounding skin. Hair-shaft thickness and distribution help distinguish broken lengths, active shedding, patterned thinning and possible scarring. A gentle hair-pull test may help assess shedding when appropriate.
More than one process can coexist: patterned thinning may accompany breakage or increased shedding. Photographs can document distribution, but cannot establish every diagnosis. An online consultation may help organise a visit to Türkiye; it does not replace the necessary examination. The final decision about diagnosis and treatment belongs to the examining physician.
Tests selected for a specific clinical question
Testing should answer a question raised by your history or examination. Screening every vitamin or hormone is not automatically useful: an abnormal result may be unrelated to the hair change. Results need interpretation alongside symptoms, diet, medicines and scalp findings.
- Blood count and ferritin: may be considered when heavy menstrual bleeding, restricted intake or other findings suggest anaemia or reduced iron stores. They do not identify every cause of shedding.
- Thyroid tests: may help when symptoms or the shedding history raise concern about thyroid function; results require clinical interpretation.
- Hormone tests: may be considered with irregular periods, increased facial hair or other signs of androgen excess, rather than ordered automatically.
- Scalp sampling or biopsy: may clarify suspected infection or scarring when inspection leaves uncertainty. These investigations answer different questions from blood tests.
Before a treatment shortlist, ask:
- Has a likely cause been identified?
- Is inflammation or shedding still active?
- Would the proposed procedure address the identified problem?
If you are considering hair transplantation for women, visible thinning alone does not establish suitability. Active scarring inflammation or diffuse donor thinning may make surgery inappropriate.
The donor examination checks density, shaft thickness and signs of miniaturisation where hair would be taken. These findings help explain what limits the donor area and graft numbers. Coverage potential differs between someone with a stable, dense donor area and someone whose donor hair is also thinning.
| Investigation | When it may be considered | What it cannot establish alone |
|---|---|---|
| Full blood count and ferritin | Diffuse shedding with possible iron deficiency, restricted intake or heavy menstrual bleeding | Whether low iron is the only reason for thinning |
| Thyroid function tests | Shedding with symptoms or a history suggesting thyroid dysfunction | Whether a separate patterned hair-loss process is also present |
| Androgen-related blood tests | Thinning accompanied by irregular periods, acne or increased facial hair | A PCOS diagnosis without the wider clinical assessment |
| Selected nutrient tests | Dietary restriction, absorption problems or other signs of a deficiency | Whether supplements would help when no deficiency is identified |
| Scalp biopsy | Suspected scarring disease or uncertainty after examination | The future response to a proposed treatment |
Treatment depends on the cause, not just the visible gap
Medical care, camouflage and selected surgical options
If tests identify iron deficiency or a thyroid disorder, care should address that problem. Supplements are not a default treatment: use them only for a demonstrated need. Inherited thinning needs a different approach, while inflammatory scalp disease may require treatment to control inflammation before considering cosmetic changes.
Topical minoxidil is an option for some forms of patterned thinning. Prescription oral treatments require individual assessment; depending on the medicine and country, prescribing for hair loss may be off-label, meaning outside its authorised indication. Ask what the proposed medicine targets and how its effects will be reviewed.
Hair fibres, wigs and styling changes can alter the appearance of thinning without treating its cause. You can also choose observation or postpone intervention, particularly while the pattern and course of shedding become clearer.
For selected women, hair transplantation for women may be considered. It redistributes existing follicles rather than creating new ones, and it does not treat every underlying cause. Planning must account for the donor supply and possible future thinning.
The terminology describes separate steps: FUE is follicle extraction, sapphire is a blade material used to create recipient openings, and DHI commonly means implantation with an implanter pen. Learning how FUE, sapphire blades and DHI differ helps you discuss a proposal without treating these labels as three interchangeable treatments.
When transplantation or particular medicines may not suit you
Temporary diffuse shedding, inadequate donor density, active alopecia areata and active scarring inflammation may make transplantation inappropriate or justify deferring it. Pregnancy, breastfeeding, blood-pressure concerns and other medicines may also restrict particular drug options. Do not start or stop prescribed treatment without discussing these factors.
Response differs between women with inherited thinning, temporary shedding and scarring loss: temporary shedding may settle after its trigger resolves, whereas scarred follicles generally cannot regrow hair. Duration, remaining follicles and control of the underlying condition also influence what treatment can achieve. A physician must examine your scalp before suitability is decided; the final decision belongs to the examining physician.
Risks and follow-up deserve space in your travel plans
Possible side effects and procedure-related complications
Before starting a medicine or booking surgery, ask which unwanted effects require stopping treatment, contacting the prescriber or seeking local assessment. The advice should name the medicine or procedure rather than rely on a general consent form.
Topical minoxidil can cause scalp irritation and unwanted facial hair. Oral medicines have different effects throughout the body and need medicine-specific counselling. Oral minoxidil, for example, can affect blood pressure and may cause dizziness, palpitations or fluid retention. Ask how your medical history affects monitoring and whom to contact if symptoms develop.
Transplantation can involve bleeding, infection, scarring, temporary shedding and altered scalp sensation. Growth may be limited or uneven, and the available donor hair constrains coverage. Discuss how complications would be assessed and managed, including after you have left Türkiye. Increasing redness, worsening pain, discharge or fever warrants prompt medical advice rather than waiting for a routine photograph review.
Continuity of care between Türkiye and home
Before travelling from France, Belgium, Switzerland or another French-speaking European country, confirm the following in writing:
- The name of the treating physician and who handles follow-up.
- Aftercare instructions in French or another language you understand.
- A contact for concerns once you return home, including arrangements outside routine hours.
- A plan for local examination if remote advice is insufficient, with access to your treatment record.
Use any supplied workflow to ask who establishes the diagnosis, why a technique is proposed and how the hairline is planned. If it describes one-year follow-up, clarify the appointment schedule, whether reviews are remote or in person, and what support is included. A follow-up schedule is not a promise of lasting density or a particular appearance.
Discuss the month-by-month course after a hair transplant alongside your travel plans, including when progress can reasonably be assessed. Ask which concerns need an examination rather than photographs alone.
When reviewing hair transplant photographs you can inspect closely, check whether lighting, viewing angle and the stage of follow-up are comparable. Selected photographs cannot predict your own outcome; they show individual examples, not the full range of possible responses.
Frequently asked questions
-
Some retinoids, anticoagulants and beta blockers can be associated with shedding, while certain chemotherapy medicines affect actively growing hairs. The timing, dose and condition being treated help your prescriber assess whether a medicine could be contributing. Do not stop or change a prescription yourself; ask the prescriber to review it with you.
-
Bring a list of medicines and supplements, relevant previous blood-test results, and a timeline of when you first noticed changes. Photographs showing your part and hairline before the change can be useful, particularly if they have similar lighting. Ask whether you should leave hair fibres or scalp concealers off for the examination.
-
You can ask, but confirm what translation or interpreting support is available before arranging travel. Request a written record of the assessment, any treatment provided, medicine names and follow-up instructions in a language you understand. Your clinician at home can then use that information if you need continuing care.
-
Follow your surgical team's written instructions for when to start washing and which products to use, because the timing depends on the procedure and scalp condition. Early washing usually involves gentle handling rather than rubbing, scratching or directing a strong water jet at the grafts. Do not pick crusts; contact the team if washing causes increasing bleeding or discomfort.
Sources
- American Academy of Dermatology
- British Association of Dermatologists
- NHS